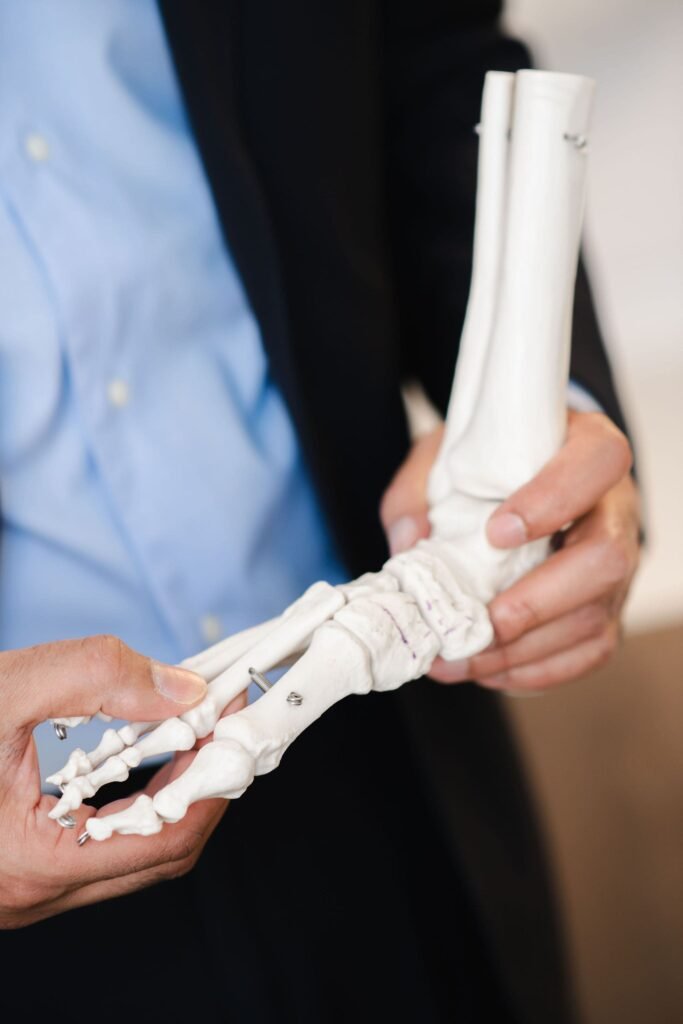
Hypermobile feet, where the joints move beyond a typical range, can make bunions harder to correct with standard techniques, which is why some patients are advised to consider a joint-fusion approach called Lapidus fusion rather than Rapid Bunion™ keyhole correction. Mr Nazir assesses joint stability before recommending either route, since the right choice depends on the condition of the joint at the base of the big toe, not on patient preference alone.For a full breakdown of how keyhole correction, Scarf/Akin, Lapidus and other techniques compare, see Bunion Surgery Techniques Explained: Keyhole, Scarf/Akin, Lapidus & More.
What Is a Bunion and How Does Hypermobility Cause One?
What does hypermobility mean in the context of bunions?
Hypermobility means a joint moves beyond its typical, stable range, and in the foot this excessive flexibility can allow the first metatarsal bone to drift out of position over time. A bunion is the bony lump that forms at the base of the big toe as this misalignment progresses. Not everyone with hypermobile joints develops a bunion, but the two are connected because instability at the base of the toe changes how forces travel through the joint. Patients concerned that their bunion may be linked to joint flexibility elsewhere in the body should raise this at consultation, since it directly affects which surgical option is appropriate.
Is hypermobility the same as having an unstable big toe joint?
Not exactly, though they are related. General joint hypermobility describes flexibility across the body, while an unstable first tarsometatarsal (TMT) joint, the joint connecting the first metatarsal bone to the midfoot, is a specific, localised instability that surgeons assess directly. It is this local instability, along with any pre-existing arthritis in that joint, that determines whether a fusion procedure is indicated. A general history of flexible joints is a useful flag for assessment, but the surgical decision rests on examination and imaging of the affected joint itself.
Comparing the Two Techniques
What is the difference between Lapidus fusion and keyhole bunion surgery?
Lapidus fusion permanently fuses the unstable joint at the base of the first metatarsal using plates and screws, and is specifically used for unstable bunion types associated with hypermobility. Keyhole bunion surgery, including Rapid Bunion™, corrects the bone position through small incisions using specialised dental-type instruments called burs, with screws placed through the same small incisions, without fusing the joint. Mr Nazir’s own clinical view is that in the majority of bunions, around 90 to 95%, keyhole correction provides durable, predictable outcomes without the need for fusion. The distinction matters because fusion is a structural, permanent change to the joint, while keyhole correction realigns the bone while preserving joint motion.
Which technique does Mr Nazir recommend for hypermobile feet?
For patients with pre-existing instability or arthritis in the first TMT joint, Mr Nazir indicates that a Lapidus fusion is the appropriate choice. For the large majority of other bunion presentations, including many with mild to moderate joint laxity, keyhole bunion surgery such as Rapid Bunion™ delivers durable results. This is not a matter of preference; it reflects an assessment of whether the joint itself is unstable or arthritic, and that assessment should be made in consultation rather than assumed from a general hypermobility diagnosis.
Can keyhole bunion surgery correct larger deformities without fusion?
Yes. Modern keyhole bunion surgery can correct larger bunion deformities without needing to fuse the joint, which reduces the risk of the bunion recurring compared to older assumptions that fusion was required for bigger corrections. This is a meaningful shift from older surgical thinking, where larger deformities were more often treated with joint-sacrificing procedures by default.
Common Misconceptions
Is it true that hypermobile feet always need joint fusion?
No, this is a common misconception. Mr Nazir notes that assumptions comparing these techniques online are often based on outdated surgical generations, and that the current evidence does not support a blanket rule that hypermobility always requires fusion. The deciding factor is whether the specific joint at the base of the first metatarsal shows instability or arthritis on examination, not a general label of hypermobility. Patients should be wary of generic online comparisons of bunion surgery types and should instead seek an individual assessment.
Does a Lapidus fusion mean losing movement in the foot?
Lapidus fusion does fuse the first TMT joint using plates and screws, which is a permanent structural change at that specific joint. The expected impact on gait and daily activity after fusion should be discussed directly with Mr Nazir at consultation.
Recovery and Long-Term Results
What counts as “long-term” success after bunion surgery?
Mr Nazir defines the critical window for recurrence as the first two years after surgery, since most bunion recurrences occur within that period. Beyond that point, if no early recurrence has occurred, long-term stability can reasonably be considered attained. He also notes that lifetime outcome data does not yet exist for keyhole bunion techniques, since the approach is newer than open surgery and fusion procedures.
Is keyhole bunion surgery a newer, less proven technique than fusion?
Keyhole bunion surgery has gone through four generations of technical refinement, evolving into the current small-incision approach using burs and screws placed through minimal incisions. It is a more recently developed approach than long-established procedures such as Lapidus fusion or Scarf-Akin, which is why lifetime follow-up data specifically for keyhole techniques is still developing. This does not mean the results are unproven within the studied window: recurrence data within the first two years, the period when most recurrences happen, supports durable outcomes in the large majority of cases Mr Nazir treats.
Who Should Consider Each Option
Am I a candidate for keyhole bunion surgery if I have flexible joints?
Possibly. Keyhole bunion surgery is suitable for most patients experiencing pain in the big toe joint affecting daily life, difficulty wearing shoes comfortably, progressive deformity, or cosmetic concerns related to foot shape. General joint flexibility alone does not exclude a patient from keyhole correction; the determining factor is whether the specific joint at the base of the first metatarsal is unstable or arthritic. An in-person assessment, including examination and imaging, is the only reliable way to confirm suitability.
What should I ask about at consultation if I have hypermobile feet?
Patients should ask specifically whether their first TMT joint shows signs of instability or arthritis, since this is the finding that separates candidates for Rapid Bunion™ from candidates for Lapidus fusion. It is also reasonable to ask how the surgeon defines long-term success and what recurrence data exists for the recommended technique. A direct conversation with Mr Nazir allows the recommendation to be based on the condition of the joint rather than generalised online comparisons.
Next Step
Patients with hypermobile feet considering bunion correction should book a consultation with Mr Nazir to have the first TMT joint properly assessed for stability and arthritis before deciding between Rapid Bunion™ and Lapidus fusion. This assessment, rather than a general hypermobility diagnosis, is what determines which technique offers the most durable outcome.