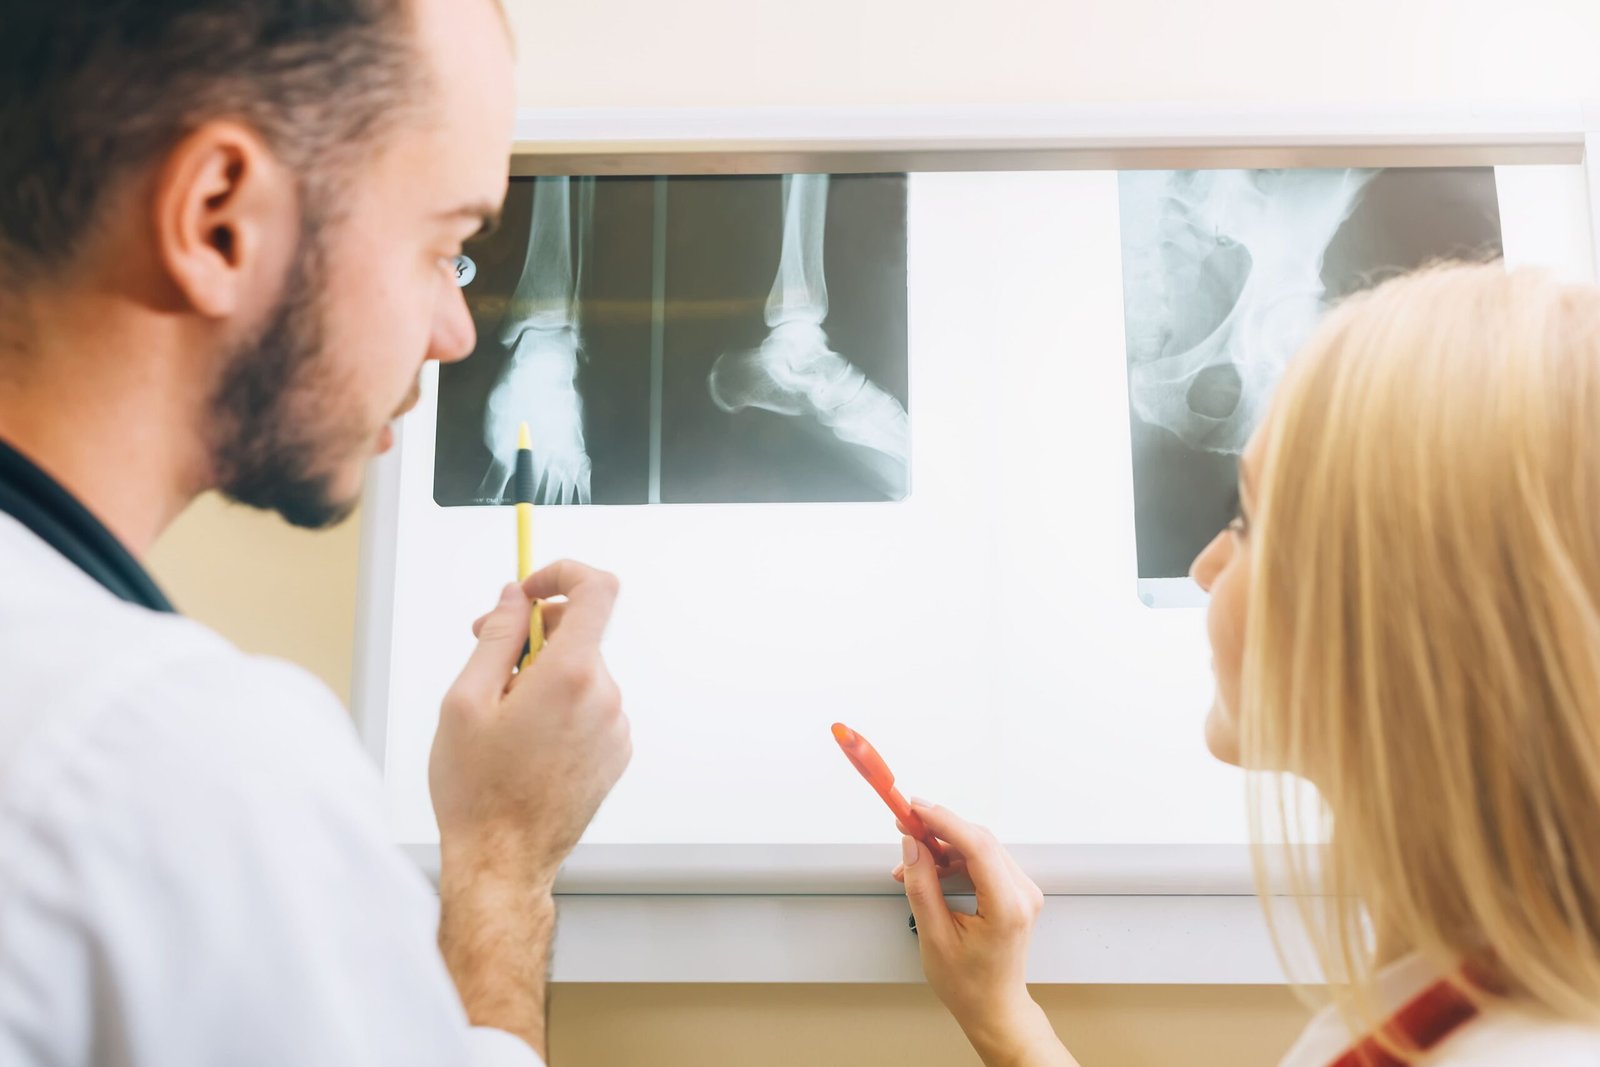
Bunion X-rays measure two specific angles — the hallux valgus angle (HVA) and the intermetatarsal angle (IMA) — to grade how far the big toe joint has shifted out of position. The IMA measures the gap between the first and second metatarsal bones, with a normal angle sitting between 7 and 9 degrees before it rises toward mild, moderate or severe classifications as the bunion progresses. These measurements, alongside a physical examination, guide whether a bunion needs non-surgical management or correction — a question Mr Nazir answers in full in Do You Need Bunion Surgery? Causes, Non-Surgical Care & Risks.
Understanding the Key Measurements
What is the intermetatarsal angle (IMA) and why does it matter?
The intermetatarsal angle (IMA) measures the degree of separation between the first metatarsal (the long bone behind the big toe) and the second metatarsal (the bone behind the second toe). A normal IMA sits at 7 to 9 degrees. Mild bunions measure up to 12 degrees, moderate bunions fall between 12 and 16 degrees, severe bunions between 16 and 20 degrees, and very severe bunions sit above 20 degrees. This angle widens as the deformity progresses, which is why repeat X-rays over time can show whether a bunion is advancing.
What is the hallux valgus angle (HVA)?
The hallux valgus angle (HVA) measures how far the big toe itself has drifted toward the second toe, relative to the first metatarsal. It is assessed on the same weight-bearing X-ray used to calculate the IMA, and the two figures are read together to grade bunion severity. A rising HVA alongside a rising IMA confirms that the deformity is a genuine structural shift in the joint rather than a soft-tissue issue.
Is a bunion diagnosed from an X-ray alone, or is an examination needed too?
Diagnosis combines a physical examination with X-ray imaging rather than relying on imaging in isolation. On examination, bunion pain is typically felt on the inside of the first metatarsal head, with normal range of motion when the big toe is moved passively, which distinguishes it from arthritis, where deep joint pain and ongoing stiffness point to cartilage wear. The X-ray then confirms the degree of bony deviation and rules out other causes of the same symptoms, such as osteophytes (small bony growths).
Can an X-ray tell the difference between a bunion and arthritis?
Yes. The distinction rests on both the imaging and the clinical findings together. Bunions show joint malalignment with preserved range of motion on examination, while arthritis in the big toe joint, including a condition called hallux rigidus (arthritis that stiffens and restricts movement in the big toe joint), shows deep joint pain, stiffness and bony growths (osteophytes) that restrict movement. A specialist examination alongside X-rays helps determine how bunions and osteoarthritis are connected and whether pain is coming mainly from soft tissue irritation, pressure over the bunion bump, joint stiffness, arthritis, or a combination of these factors.
Can an MRI or ultrasound be used instead of an X-ray?
X-ray remains the standard first step, but MRI or ultrasound can add useful detail in some cases, particularly where an injury is suspected alongside bunion symptoms. Medical imaging such as X-ray, ultrasound or MRI can show whether the joint has alignment issues or osteophytes, helping confirm a diagnosis. This is relevant because the first metatarsophalangeal (MTP) joint carries 40–60% of body weight during normal walking, with these forces increasing further during sport, so injury-related symptoms can sometimes mimic bunion pain.
What the Numbers Mean for Treatment
Does a higher IMA or HVA number mean surgery is automatically needed?
Not automatically. Severity measurements from X-ray describe how far the joint has shifted, but the decision to operate depends on symptoms, impact on daily life and other health factors, not the angle alone. There is no fixed rule for whether surgery is the right treatment, and factors to weigh include the level of symptoms, the impact on daily activities and quality of life, and any other health conditions that might affect surgical eligibility. A patient with a moderate IMA but significant pain may be a better surgical candidate than someone with a higher angle but minimal symptoms.
What treatment options exist once a bunion is confirmed on X-ray?
Early-stage, less symptomatic bunions are usually managed without surgery, through measures such as larger, more accommodating shoes, protective cushioning, toe spacers and splints, and bespoke orthotics (custom-made shoe inserts). Once a bunion is impacting daily life or has progressed significantly, treatment options move toward minimally invasive or open osteotomy procedures (surgery that realigns the bone). Minimally invasive correction typically uses small screw fixation to hold the realigned bone in place.
Can X-rays show whether the bunion bump or the joint itself is causing the pain?
Yes, this is one of the main reasons imaging is combined with a specialist examination. Assessing the joint helps determine whether there is arthritis present, whether the pain is coming mainly from the bony bump or from the joint itself, and which treatment options may be suitable, building a treatment plan based on the underlying cause of pain rather than the symptoms alone.
Will my X-ray show if the bunion is going to keep getting worse?
An X-ray is a single snapshot, so progression is better tracked by comparing imaging over time. Bunions naturally tend to progress over a period of years, and while this progression cannot be stopped completely, it can be slowed through measures such as supportive footwear and orthotics. Patients concerned about progression should ask whether a repeat X-ray at a future date would help track any change in the IMA and HVA.
Is it a misconception that a visible bump means the bone is definitely misaligned?
Yes, this is a common misunderstanding. A visible bump can result from soft tissue swelling, pressure irritation or joint inflammation, not only from bony deviation, which is why a specialist examination and X-ray are used together to separate these causes rather than relying on visual appearance alone. The X-ray measurements of the IMA and HVA provide the objective confirmation of true bony malalignment, distinct from swelling that can make a joint look more prominent than it is.
Do children and teenagers get the same X-ray assessment for bunions?
The same imaging principles apply, but treatment decisions differ significantly by age. Early intervention in children or preteens is generally avoided, as the evidence supporting surgery before the growth plates have fused is poor, meaning surgical correction is typically delayed until at least age 16 even when imaging confirms a deformity. Younger patients are instead managed conservatively while growth continues.
Does family history or footwear show up differently on an X-ray?
X-rays measure the current angles rather than the cause, but both genetics and footwear are recognised contributors to the deformity shown on imaging. A strong family history is common among bunion patients, and footwear choices, particularly high heels or unsupportive flat shoes with little structural support, are frequently reported alongside symptomatic bunions. Genetics is considered the main underlying cause, with an evolutionary basis linked to changes in the function of the big toe over time, and bunions are understood to affect around a quarter of the world’s population, with women more commonly affected due to traditional footwear choices.
What should happen after an X-ray confirms a bunion?
Once X-ray and examination findings confirm a bunion, the next step is a specialist consultation to translate the IMA and HVA measurements into a personalised treatment plan. Anyone experiencing bunion pain should see a podiatrist or doctor for a formal assessment, since diagnosis of both different types of bunions and bunionettes (a similar deformity affecting the little toe) is confirmed through X-ray. Patients can book a consultation with Mr Nazir to review their imaging and discuss whether non-surgical care or correction with Rapid Bunion™ (Mr Nazir’s trademarked minimally invasive bunion correction protocol) is the appropriate next step.